Offshore Admin for Australian Clinics: What Moves, What Stays at the Front Desk, and How to Keep Patient Data Safe
Offshore admin works for Australian clinics when it takes the back office: what can move, what stays local, and the privacy steps to sort out before anyone logs in.
20 July 2026
Offshore admin works well for Australian clinics when it takes the back office: incoming mail, recalls, referral drafts, billing follow-ups and chasing. A medical virtual assistant can own all of that from overseas. The front desk and anything urgent stay local, and every clinical decision stays with the clinician.
In my experience, the order is where it goes wrong. Clinics hire first and sort out access and privacy later. A clinic holds health information, so the privacy rules apply to it whatever its size, and they apply before anyone logs in from overseas.
So my advice is simple. Move the back office. Keep anything in person or urgent local. Set up access and privacy before the first login.
The short version
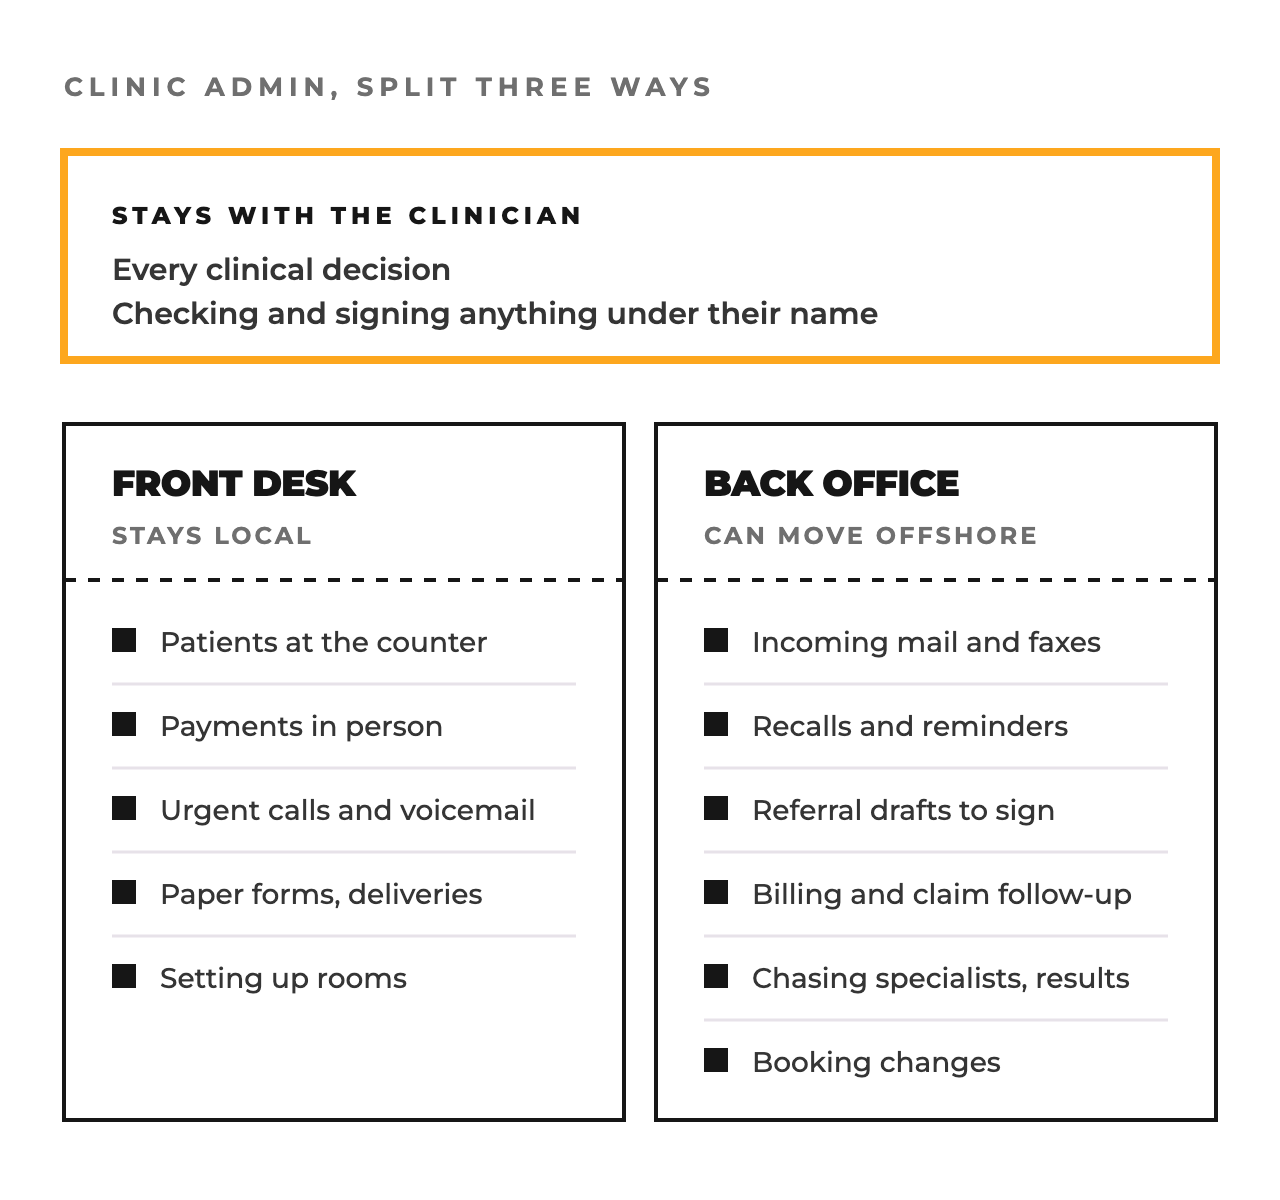
- What can move offshore: incoming mail and faxes, recalls and reminders, referral letters drafted for the clinician to sign, billing follow-ups, booking changes, and chasing specialists and missing paperwork.
- What stays local: the front desk, anything a patient does in person, voicemail, and any call where a patient may need help now.
- What stays with the clinician: every clinical decision, and checking and signing anything that goes out under their name.
- What the law asks: under the Privacy Act, take reasonable steps (usually an enforceable contract) before disclosing information overseas, say in your privacy policy that it may go overseas, and know that you stay accountable. Clinics in NSW, Victoria and the ACT also have state or territory health privacy laws.
- Why clinics do it: 77% of GPs are dissatisfied with the amount of admin in their work (RACGP, 2025). In my view, allied health clinicians carry much the same load.
What a medical virtual assistant can do for a clinic
In my view, most back office admin can be done from anywhere by someone organised, with the right access and a clear list of what’s theirs.
- Incoming mail. Sorting incoming letters, results and faxes and filing each one to the clinician who requested it. The assistant files; the clinician reads and decides.
- Recalls and reminders. Running the recall list and booking the follow-ups the clinician has asked for.
- Referrals and letters. Drafting from templates once the clinician has decided, sending, and confirming the other practice has them.
- Billing follow-up. Unpaid invoices, rejected claims and missing paperwork, through whatever systems the clinic already uses.
- Chasing. Specialists who haven’t booked, results that haven’t come back, forms that haven’t been returned.
That last one is bigger than it looks. In about one in three businesses we’ve mapped, a large share of the work being handed over was chasing people.
In one health practice, email filters kept putting important faxes in the newsletter folder, so the owner checked folder after folder every day. The fix was an assistant reading each email and labelling it.
Can a virtual medical receptionist answer your phones?
Some of them, in my view. I’d keep the first answer and the voicemail local. A patient who needs help now should reach someone in the clinic who can walk down the corridor to a clinician, and an urgent message shouldn’t wait in a queue overseas.
What can move is the admin side of the phones: call-backs the clinic has already marked as admin, such as booking changes, forms and payments. The front desk decides what goes on that list. The offshore assistant works through it.
What stays at the front desk
- Patients at the counter. Check-in, payment, the conversation about the next appointment.
- Urgent calls and voicemail. Anything that might be clinical goes to someone in the building.
- Anything physical. Paper forms, deliveries, the room that needs setting up.
What stays with the clinician
Every clinical decision, without exception: what a result means, what goes in a plan, whether a referral is needed. The assistant prepares, files and chases. The clinician decides, checks and signs.
In nearly two in three businesses we’ve mapped, owners handed over the doing and kept the deciding. In a clinic, the deciding is every clinical call.
Is it legal to use offshore admin in an Australian clinic?
It can be. Under the Privacy Act, these are the points the OAIC guidance sets out.
Clinics are covered whatever their size. The small business exemption (turnover of $3 million or less) does not apply to health service providers that hold health information. A two-room physio clinic has the same Privacy Act obligations as a large practice.
Sending information to an overseas contractor is generally a disclosure. Under Australian Privacy Principle 8, before you disclose personal information to an overseas recipient, you must take reasonable steps to make sure they handle it in line with the Australian Privacy Principles. The OAIC generally expects that to mean an enforceable contract. In limited cases, where the clinic keeps effective control of the information, the guidance says it may count as a “use” instead. I wouldn’t plan on that. Set up as if it’s a disclosure.
When it’s a disclosure, you stay accountable. If the overseas recipient mishandles the information in a way that would breach the principles, the clinic is accountable for it.
Your privacy policy has to say so. Under APP 1, it must state whether information is likely to go to overseas recipients and, if practicable, which countries.
Some states add their own rules. In NSW, Victoria and the ACT, private health service providers must also comply with state or territory health privacy laws.

How I’d set it up
Limit access to what the work needs
The role will see some health information, such as letters and results, which is why the privacy steps apply. Give access to the systems the work needs, and widen it only when a task needs more.
Keep everything in your systems
The assistant works in the clinic’s practice software, email and storage, with their own login. No copies on personal devices, and no outside tools the clinic hasn’t approved. In the same health practice, an outside AI email tool was considered and turned down because of where it stored data. That’s the right instinct.
Plan for checking
Offshore or local, software often still needs checking. In just over half the businesses we’ve mapped, automation still needed a person to check it. Build that checking into the role.
Keep a simple view of what’s been handed over
In that practice, the owner tracked what had been delegated through simple lists, such as a daily invoice list and an approvals list. A short list of what’s waiting on the clinician is usually all they need to see.
My view: offshore admin takes the work around patients
I’d treat offshore admin as a list. Go through one week of non-clinical work, task by task, and mark each one: needs a clinician, needs someone in the room, or needs neither. The third pile is the offshore role. Our free work tracker helps with the logging.
Then sort out the privacy steps before the first login. Done in that order, the clinician gets hours back, and recalls and letters go out on time.
Where HIPPO fits
HIPPO places offshore admin support with health and allied health clinics. In a clinic, that role can own incoming mail, recalls, referral drafts, billing follow-up and chasing. The front desk stays local, and your clinicians keep every clinical decision.
If your clinicians are doing admin between patients, book a call with me. We’ll sort your back office into what moves and what stays, and pick the first role. Your Role Plan follows, so your team can see what comes off their day.
Ready to build
your back office?
Book a call with Dusty. We work out the first role to hire, and afterwards you get your Role Plan in writing.
Related articles

Allied Health Is Short on Clinicians. The Fastest Fix Isn't Hiring One.
Can't recruit another clinician? Here's how allied health clinics reclaim client-facing hours by moving non-clinical admin off clinicians' plates.

When Admin Makes Clinicians Quit: Redistributing Non-Clinical Work in Australian Practices
GP admin burden is now the top reason clinicians plan to leave practice. Here's how practices are separating judgement from paperwork and redistributing the load.

From Billing Chaos to Clean Ledgers: How Allied Health and NDIS Providers Build a Repeatable Billing and Reconciliation Engine in 2026
Multi-payer billing across NDIS, Medicare, DVA and private health funds creates predictable failure points. Here is the task scope and daily rhythm for a structured billing coordinator role.