GP Admin Burden: Where It Comes From and What a Practice Can Take Off the GP's Desk
77% of GPs are dissatisfied with their admin load, and in 2024 it was the top reason GPs gave for planning to stop practising. Where it comes from, and how to move it safely.
31 August 2026

More than three-quarters of GPs (77%) are dissatisfied with the amount of admin attached to their work. That’s from the RACGP’s Health of the Nation survey in 2025, up from 70% the year before. In the 2024 survey, admin workload was the top reason GPs gave for planning to stop practising within five years.
Some of that load sits with government, and only policy will fix it. The rest sits inside the practice. In most practices, the GP does the clinical decision and all the paperwork wrapped around it. Nobody ever split the two.
In my view, that split is the fastest fix a practice owner controls. The GP touches the decision. Someone else handles everything before and after it.
The short version
- How big is it: 77% of GPs are dissatisfied with their admin load, and 69% report burnout (RACGP, 2025).
- Why it matters: admin was the top reason GPs gave for planning to stop practising. Two in three (66%) said less compliance work would encourage them to keep working longer (RACGP, 2024).
- How much time: no recent Australian figure in hours. A New Zealand study reported in 2026 found GPs spent 31% of their time, about 12 hours of a 40 hour week, on clinical work without the patient there.
- Where it comes from: authority prescriptions, clinical paperwork like care plans and correspondence, and Centrelink and WorkCover forms, the areas GPs said could be improved (RACGP, 2025).
- What a practice can do: split each task into the clinical decision and the paperwork around it. Give the paperwork to one person, and have the GP check anything that goes out.
How much time do GPs spend on admin?
We couldn’t find a recent Australian measure in hours. The closest is a study of 566 New Zealand GPs, reported by the RACGP’s newsGP in February 2026. It found GPs spent 56% of their time with patients and 31% on clinical work done without the patient there. Across a 40 hour week, that’s about 22 hours of consults and 12 hours of work behind the scenes.
That second number is the one that matters for a practice owner. Results, letters, referrals and forms happen when the patient isn’t in the room. In the New Zealand study, that work was unfunded. The RACGP’s president put it simply: if the patient isn’t in front of you, you’re not being paid.
So it lands in the gaps: between patients, after the last appointment, on Sunday night. The practice sees the appointment book. It rarely sees the hours underneath it.
Where the GP admin burden comes from
When the RACGP asked GPs which admin tasks could be improved, authority prescriptions led at 44%, with clinical admin at 36% and Centrelink and WorkCover forms at 30%.
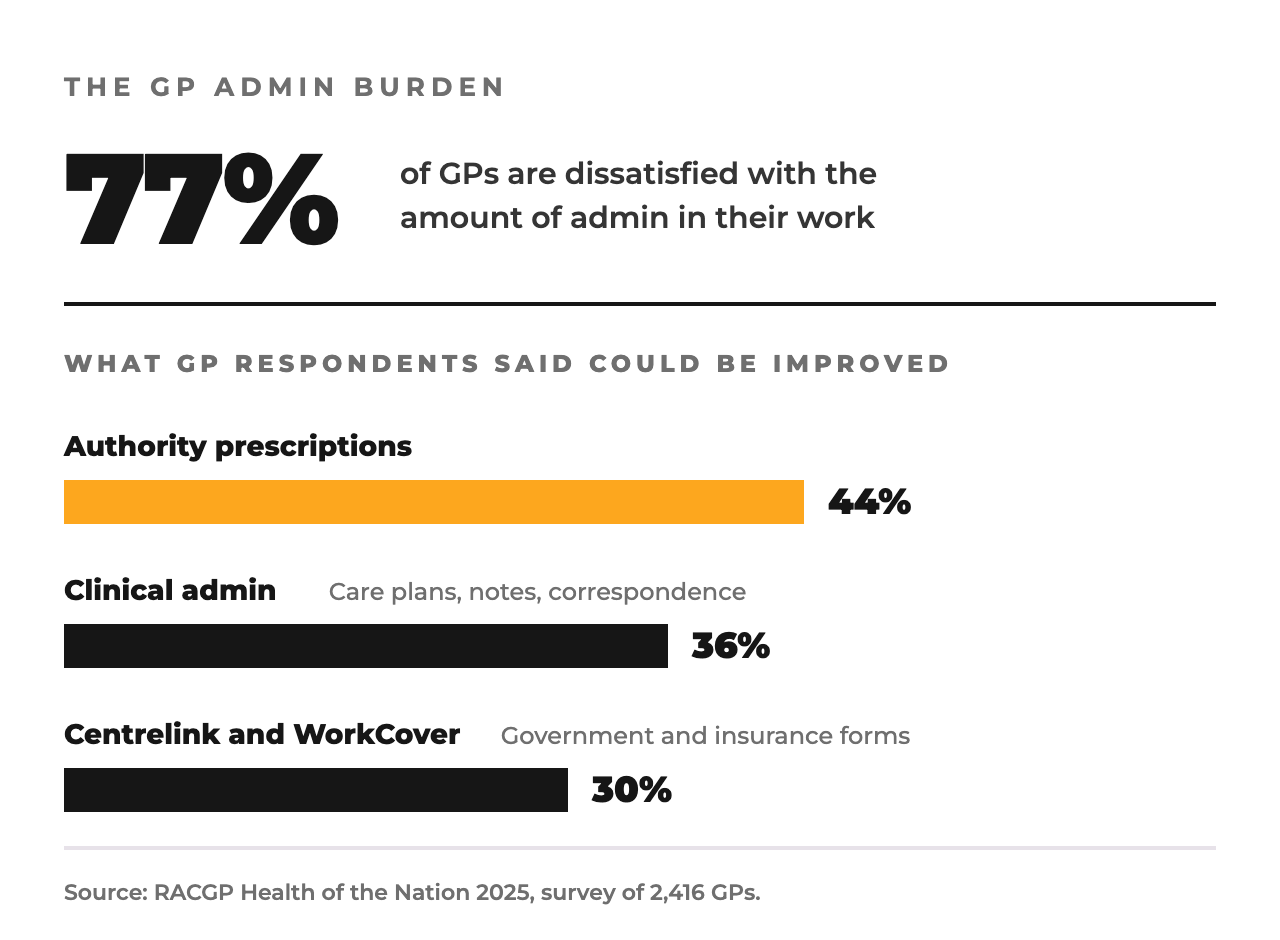
Authority prescriptions. The biggest single complaint, named by 44% of GPs. In my view, this one mostly stays with the GP, and the fix sits largely with government.
Clinical admin. Named by 36%: note taking, mental health and care plan paperwork, and aged care correspondence. A lot of this is a GP decision wrapped in paperwork. The GP decides what goes in the plan. In my view, preparing the template, booking the reviews and sending copies to the right people doesn’t need a doctor.
Government and insurance forms. Named by 30%, with Centrelink and WorkCover as the examples. In my experience, much of a long form repeats information already in the patient’s file. The GP’s part is the clinical opinion and the signature.
Around those three sits the work nobody counts. Incoming results and letters. Recalls and reminders. Chasing a specialist who hasn’t booked the patient.
What needs a GP, and what doesn’t
Take one specialist referral. It looks like a single task. Laid out step by step, it’s ten, and only the deciding and the checking need the GP.

The same pattern shows up across most GP admin:
- Results: every result goes to the GP, who reviews it and decides what happens next. Matching it to the patient record, booking the follow-up the GP asks for and recalling the patient are admin.
- Care plans: the GP decides the plan. Preparing the template from the record, booking reviews and sending copies are admin.
- Forms: the GP gives the clinical opinion and signs. Filling in details already on file and chasing missing information are admin.
- Referrals: the GP decides and checks the letter. Drafting it from a template, sending it and chasing the appointment are admin.
Most practices have the GP doing both halves of every task like this. Split them and the GP’s part shrinks to the parts only a GP can do.
How to reduce GP admin without adding clinical risk
Put a GP check before anything goes out
Anything that leaves the practice under the GP’s name gets a GP check first. No exceptions on a busy day. The admin person drafts; the GP reads and signs. That one rule removes most of the risk people worry about when they think about handing clinical paperwork to someone else.
Write the escalation rule down
The admin person needs one written rule: they never decide what anything clinical means. Every result goes to the requesting GP, whatever it says. A form asking a clinical question goes to the GP. Anything they’re unsure of goes to the GP. The rule is what makes delegation safe, so write it down.
Fix the inbox before anything else
A lot of GP admin starts with something arriving: a result, a letter, a fax. In one health practice we worked with, the email filters kept sending important faxes into the newsletter folder. The owner ended up checking folder after folder, every day, in case something had been missed. The fix was a person reading each item and labelling it.
That’s common. In just over half the businesses we’ve mapped, automation that was meant to save time still needed a person to check it. In a practice, an inbox nobody fully trusts is a clinical risk.
Make one person own the chasing
Specialists who haven’t booked, results that haven’t come back, patients who missed a recall. In about one in three businesses we’ve mapped, a large share of the work being handed over was chasing people. In my experience, it’s the work most likely to fall through the cracks in a practice, because it belongs to nobody. Give it to one person with a list.
My view: the GP should touch the decision and nothing around it
Most practices try to fix GP admin with software first. New templates, an AI scribe, an auto-filing rule. Some of it helps. The admin still lands on the GP until someone decides who does what.
Go through one week of GP admin, task by task, and mark the clinical decision inside each one. Everything around it belongs to someone else, with a GP check before anything goes out.
This split is also safer. When one person owns incoming mail, the recalls and the chasing, less of it waits for a GP to get to at night.
In nearly two in three businesses we’ve mapped, owners handed over the doing and kept the deciding. In a practice, the deciding is every clinical decision. It never moves.
What to hand over, and what to keep
Hand over:
- reading and labelling incoming letters and faxes, matching results to the patient record, and sending them to the right GP
- recall and reminder lists, and booking the follow-ups
- drafting referral letters from templates once the GP has decided
- preparing care plan and form paperwork from the record for the GP to complete and sign
- chasing specialists, labs and missing information
- sending copies and confirming they’ve arrived
Keep with the GP:
- every clinical decision, including what a result means and what happens next
- authority prescriptions
- the clinical content of plans, forms and reports
- checking and signing anything that goes out under their name
The practice also decides what the admin role can see and do in your clinical software.
Is admin support worth it for a general practice?
Count one week first. Ask each GP to note every admin task they do outside consults and how long it took, then mark which ones needed their clinical judgement. Our free work tracker makes this quick, and it totals the week. If the log shows hours a week of filing, chasing and form-filling, that’s time the GP could spend with patients, or not spend at night.
The second test is what it costs in GPs. In 2024, admin was the top reason GPs gave for planning to stop practising. Two in three said less compliance work would encourage them to keep working longer. In my view, replacing a GP costs far more than redesigning their week.
We’ve also written a task-by-task playbook for shifting forms, recalls and follow-ups off GP desktops.
Where HIPPO fits
HIPPO places offshore admin support with health and allied health practices. In a general practice, that role could own incoming mail, recalls, referral drafts and chasing, while your GPs keep every clinical decision.
Owners often come to me wanting one person to fix everything at once. The better start is the one role that gives your GPs the most time back.
On a call, we work out what that role is. Afterwards you get your Role Plan: where the practice is stuck, the role to hire first, and what stays with your GPs.
Ready to build
your back office?
Book a call with Dusty. We work out the first role to hire, and afterwards you get your Role Plan in writing.
Related articles
Admin in General Practice in 2026: A Playbook for Shifting Forms, Follow-Ups and Recalls Off GP Desktops
70% of GPs say admin is driving them out of practice. Here is a concrete task-by-task playbook for shifting forms, recalls, triage and billing queries to structured admin roles.

AI Admin Agents Are in Australian Clinics Now: Where the Human Layer Still Has to Sit
Australian clinics are already running AI agents for documents, calls, and billing. Here's where they fail and what human role has to sit alongside them.

When Admin Makes Clinicians Quit: Redistributing Non-Clinical Work in Australian Practices
GP admin burden is now the top reason clinicians plan to leave practice. Here's how practices are separating judgement from paperwork and redistributing the load.